
 Post-ERCP pancreatitis (PEP) remains an important consideration surrounding ERCP procedures. As clinicians continue to evaluate strategies for reducing this risk, research has reinforced the role of prophylactic pancreatic duct stenting.
A recent 2026 study examined data from 18 randomized controlled trials involving 4,637 patients to evaluate whether prophylactic pancreatic duct stenting can help prevent PEP. The findings showed a significantly lower risk of PEP with stent placement compared with no stent placement.
Pancreatic anatomy is anything but a straight path. Navigating the pancreatic duct means accounting for its natural twists, turns and varying anatomy.
In a separate publication, Dr. Martin Freeman discussed pancreatic stenting for PEP prevention and highlighted the importance of stent characteristics, including the use of soft, flexible materials.
This shifts the conversation beyond simply whether a stent is placed and toward the characteristics of the device being used.
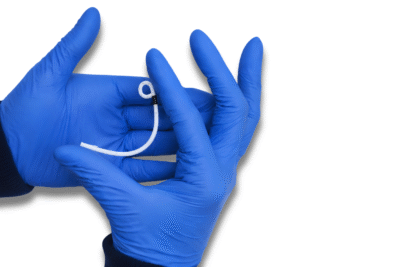
The Freeman Pancreatic Flexi-Stent was developed with these considerations in mind. Its soft, pliable construction is designed to accommodate the twists and turns of pancreatic anatomy while supporting drainage.
For clinicians, this brings two pieces of evidence into the same conversation: research supports pancreatic stent placement as a strategy for reducing PEP risk, while separate clinical discussion highlights the importance of characteristics such as softness, flexibility and design.
The evidence supporting prophylactic pancreatic stenting gives us an important starting point. But prevention is not simply a question of stent versus no stent. It also encourages a closer look at the device being placed and how its design relates to the anatomy in which it needs to function among.
So… If stent placement can help reduce the risk of post-ERCP pancreatitis, shouldn’t the stent itself matter too?
Bucheeri et al. Pancreatology. 2026.
Freeman ML. Gastroenterology & Hepatology (NY). 2015.
